Measles did not “return” because the virus changed; it returned because our collective immunity thinned just enough, in just the right places, to let an imported spark become sustained domestic fire.
At a Glance
- National kindergarten MMR coverage has fallen below the 95% threshold for outbreak prevention four years running, creating gaps large enough for spread.
- Recent U.S. surges were dominated by unvaccinated or undocumented-status patients, with outbreaks clustering where local coverage sagged far under the national average.
- Measles elimination hinges on stopping continuous, homegrown transmission; once that persists 12 months, the “measles-free” label is lost.
- Resurgence reflects interacting forces: uneven vaccination, imported index cases, clustered susceptibility, and delayed recognition—multicausal, but with immunity as the central lever.
Elimination, defined precisely—and why the threshold matters
In epidemiology, “elimination” is a surveillance term with a hard edge: no endemic transmission for at least 12 consecutive months, documented under an adequate surveillance system. It never meant zero cases; travel can and will reintroduce measles. The burden of proof is whether the virus, once imported, sustains itself domestically for a full year—evidence that community immunity has slipped below the level required to snuff out chains of spread. The Centers for Disease Control and Prevention (CDC) applies that definition, and regional verification bodies review the data to affirm or revoke a country’s status. The practical implication is straightforward: if outbreaks keep relinking into a continuous chain, the “measles-free” designation cannot hold.
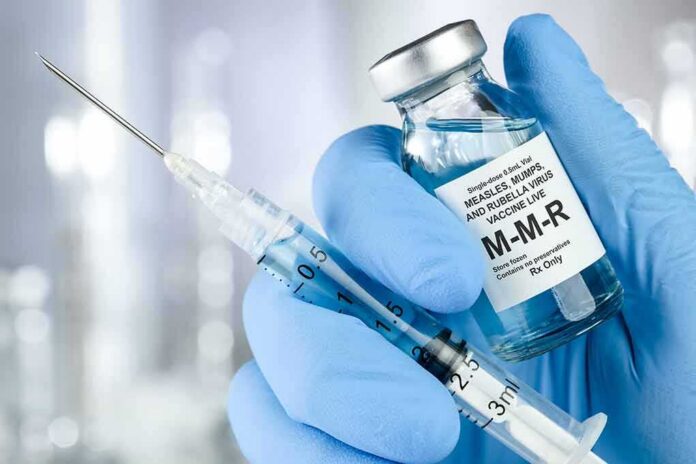
That standard is demanding because measles is. With a basic reproduction number often cited well above 10, even small pockets of susceptible people can keep the virus in circulation. The proven countermeasure is high, even coverage with two doses of measles-mumps-rubella (MMR) vaccine—about 97% effective—delivered widely enough that imported sparks fail to take.
The immunity gap: national averages down, local pockets deeper
By the CDC’s own accounting, national kindergarten MMR coverage has now sat below the 95% outbreak-prevention benchmark for four consecutive school years; in 2023–24 it was 92.7%, beneath the Healthy People 2030 target. That seemingly small 2–3 point slip at the national mean equates to hundreds of thousands of susceptible young children and is more than enough to expose pockets where coverage is far lower. The decline is measurable against the pre-pandemic baseline: kindergarten MMR coverage dropped from 95.2% in 2019–20 to roughly the low 92% range by mid-decade, leaving an estimated 280,000 kindergartners at risk in the 2025–26 cohort alone.
Those national figures conceal the geography of vulnerability. In Texas—a state that saw a substantial 2025 outbreak—kindergarten coverage in affected local areas ranged from 77.3% to 94.6%, despite a statewide figure around 93%. Outbreaks materialized where those local deficits lined up with exposure opportunities, not uniformly across the map. This is the canonical pattern of post-elimination resurgence: the virus exploits uneven immunity more than national means.
Who became ill: the vaccination ledger in outbreak investigations
When investigators reconstruct chains of transmission, vaccination status tells the story of susceptibility. In the Texas outbreak, 201 of 207 confirmed patients—97%—lacked documented MMR vaccination or had unknown status. Public-health practitioners group “unknown” with “unvaccinated” not to blur motives but because, in an acute response, the absence of reliable documentation signals uncertain protection and a need for rapid immunization and post-exposure actions. Across the U.S. surge, most cases were outbreak-associated rather than isolated imports; in 2025, 90% of 2,289 U.S. measles cases were tied to outbreaks, and by 2026 the CDC tallied 5,412 cases and 43 new outbreaks, with 96% of cases outbreak-associated—evidence of sustained domestic spread once the virus landed.
None of this requires asserting that vaccination decline single-handedly caused every chain. Importations seeding the first case, delays in diagnosis, structural access barriers, and social clustering all modulate whether a virus keeps spreading. But in a pathogen with measles’ transmissibility, falling and uneven coverage is the enabling condition; it converts sparks into fires.
Mechanism: why 95% is not a slogan but a system property
Herd immunity is not a moral argument; it is a network property arising from contact patterns, vaccine effectiveness, and the virus’s reproductive potential. For measles, the threshold is high because each case, in a fully susceptible population, can infect a dozen or more others. Two-dose MMR effectiveness near 97% still leaves a small proportion of vaccinated individuals susceptible; if coverage slips and susceptible people cluster—say, in a school, congregation, or neighborhood—those residual vulnerabilities connect, and the virus finds runway. The 95% target is therefore not a bright line of perfection but a practical buffer: above it, most importations sputter; below it, the risk of prolonged chains rises steeply.
The Texas coverage range illustrates how local structure dominates national averages. A district at 77% two-dose coverage does not merely invite a few more cases; it reconfigures the contact network so that a single introduction can traverse many households and settings before it is recognized. That is exactly what the outbreak data show.
How elimination is gained, lost, and regained
Historically, the United States achieved measles elimination in 2000 through a layered approach: strengthening routine pediatric immunization, implementing and enforcing school-entry requirements, improving surveillance and laboratory confirmation, and moving from a one-dose to a two-dose schedule. Those gains are resilient but not permanent. The regional verification process, housed at the Pan American Health Organization (PAHO), applies the 12-month criterion to determine whether a country continues to interrupt endemic transmission and whether its surveillance is robust enough to say so confidently. CDC’s definition and the PAHO framework align on these points: when domestic chains connect long enough to exceed a year, elimination is, by definition, lost until sustained interruption is re-established and verified.
Practically, regaining status requires closing immunity gaps—raising two-dose coverage to, and ideally above, 95% where people live and learn—while also tightening the other links in the chain: rapid case recognition, lab confirmation, isolation, post-exposure prophylaxis, and targeted vaccination in underimmunized communities. Verification follows performance, not promises.
🚨 U.S. MEASLES CRISIS: 5,412 CASES — 10 DEATHS REPORTED AS OUTBREAKS SPREAD
🇺🇸 UNITED STATES | NOVEMBER 15, 2026
The United States is experiencing its largest measles resurgence in 35 years, with more than 5,400 confirmed cases and a rising death toll.According to CDC data… pic.twitter.com/DXQ01Y61LS
— Adam Genesis 💒 🙏 ✝️ 🔥 Navigating the Last Days (@AdamGenesisEden) November 15, 2026
What the numbers do—and do not—say about causation
The surveillance record supports clear, load-bearing conclusions. Coverage fell from a pre-pandemic plateau; outbreak growth concentrated among people without documented vaccination; affected locales displayed materially lower coverage than their states as a whole; and the majority of cases aggregated into outbreaks rather than remaining isolated importations. Those are the core drivers of elimination risk. At the same time, an expert reading respects what the data cannot apportion precisely without additional reconstruction: how much each factor—importation pressure, access barriers, intentional refusal, delayed diagnosis, or reporting dynamics—contributed to any specific chain. The right synthesis is multicausal, with population immunity as the principal control knob.
The path back to durable control
Preventing the next year of transmission hinges on closing coverage gaps where people actually congregate. That means auditing and addressing subcounty underimmunization, making vaccination easy in the hours and places families use, tightening school-entry enforcement, and deploying rapid, community-embedded vaccination in outbreaks. It also means improving documentation—linking immunization registries with clinics and schools—so “unknown” becomes “vaccinated” when warranted, and susceptible individuals can be reached quickly when it is not. None of these steps are speculative; they are the same playbook that delivered elimination in the first place.
Sources:
msn.com, cdc.gov, tools.cdc.gov, iris.paho.org












